
I have always been fascinated by the clinical application of massage therapy. One of the leading scientists in the field of modern Medical Massage therapy, Prof. Aksenova, MD, once stated:
“The treatment of ANY disorder of the human body has to include the appropriate method of massage therapy.”
During my professional career, I have witnessed many times how true this statement is. However, even after years of practicing, studying and teaching, the clinical potential of massage therapy still surprises me. The purpose of this article is to share with readers one such example I recently witnessed. It started with a member of my family.
For a few years, my father-in-law had complained of a dry eye sensation, and recently it became so bad that it started to affect his vision. According to him it was as if he were seeing images through a thin film.
He went to ophthalmologists in Odessa, Ukraine, and was diagnosed with a condition called Dry Eye Syndrome. Prescribed treatment didn’t work. He tried various eye drops, hot compresses, medications, and even probing, but his condition worsened. When he visited the US, we consulted with an ophthalmologist here. The same diagnosis was confirmed, and similar treatments again didn’t produce any results. I also used Eye Therapy on him, which is part of the MEDICAL MASSAGE PROTOCOL for Headaches, but also without any success.
Several months ago, he called and cheerfully informed us that he had completely recovered and all symptoms were gone. We were very happy for him and I asked what therapy finally helped him. To my complete surprise, he said that a special massage of his eyes had entirely eliminated symptoms of Dry Eye Syndrome and restored his vision. Of course, I asked for details, since I had never heard of such an application.
To fully understand the therapy we will discuss below, we need to look into the cause of Dry Eye Syndrome. On the upper and lower eyelids we have special sebaceous glands which produce oil. These glands were discovered by the German physician Heinrich Meibom in 1666, and they were named the Meibomian glands after him.
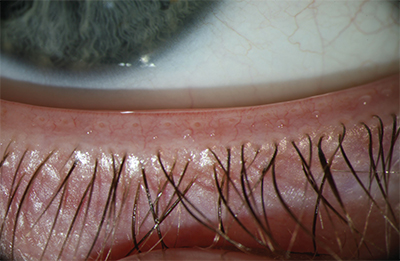
The openings of these glands are located at the bases of the eyelashes. On average, there are about 25-40 of these glands in the upper eyelid and 20-30 in the lower eyelid. Fig. 1 illustrates the openings of the Meibomian glands on the lower eyelid.
The oil which is secreted by these glands is called Meibum and it plays a critical role in the normal function of the eye since it:
- Spreads tears in a thin film which covers all surfaces of the eyeball
- Prevents quick evaporation of the tears from the sclera of the eyeball
- Prevents spillage of the tears onto our cheeks
- Keeps our eyes airtight at night
- Protects our eyes from dust, working together with the eyelashes
To accomplish these complex functions, Meibum has a very elaborate composition of 100 major lipids, over 90 proteins and electrolytes (Shrestha et al., 2011). Every time we blink and our orbicularis oculi muscle contracts, a tiny portion of Meibum is released into the eye, maintaining the tear film (Linton et al., 1961). Fig. 2 illustrates the composition of the tear film.
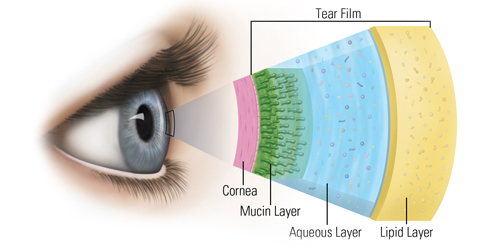
As you can see in the picture above, Meibum forms the outer layer of the tear film (marked ‘Lipid’ in the picture) and it protects its inner layers, allowing the eye to function properly.
Dry Eye Syndrome is a condition in which the Meibomian glands do not secrete enough oil or the secreted oil is of poor quality. If gland openings get clogged, less oil comes out, and this greatly affects eye function, since tears quickly evaporate. Also, clogging of these glands may trigger a condition called Blepharitis, which is inflammation of the eyelids.
The widely accepted treatment protocol consists of artificial eye lubricants, topical steroids, fish oil, warm compresses, self-massage of the upper and lower eyelids and treatment with pulsed light. A more aggressive treatment is Meibomian gland probing. It is conducted by an ophthalmologist who, after applying anesthetic eye drops, uses a hand-held instrument to manually dilate the openings of each Meibomian gland. However, all of that may not eliminate the clogging of the glands.
Recently, special forceps for ophthalmologists to drain Meibomian glands were introduced. Here is a video which illustrates the application of the forceps. It is also a great illustration of clogged Meibomian glands, since you can closely observe their drainage by the forceps.
Meibomian Gland Forceps expressing left eye. – YouTube
Let’s come back to the story about my father-in-law now. After months of searching, he went to an eye clinic where a simple massage procedure had been used for years to drain Meibomian glands long before forceps were even developed. It is less unpleasant and is usually conducted by a specially trained therapist.
The video below illustrates the drainage of Meibomian glands conducted by a therapist at the Tarus Ophthalmological Center in Odessa, Ukraine. The head of the center is Prof. Sergei Shchipun, MD.
This is not a treatment therapists are supposed to do alone in their office. It is a medical procedure which is done by a specially trained therapist who works in an ophthalmological clinic. The intention of this article and video is to show how wide the clinical application of massage therapy is. The comments in the video are in Russian, and I will briefly describe the steps you see and comments by the therapist in the video:
- The therapist places two drops of anesthetic in each eye before the procedure and shows the vial.
- The therapist opens the sterile package with an eye probe, which is a glass stick with one flat end. It is used in ophthalmology to precisely place medications in different parts of the eye. Fig. 3 illustrates the eye probe used in the video for the drainage of Meibomian glands.
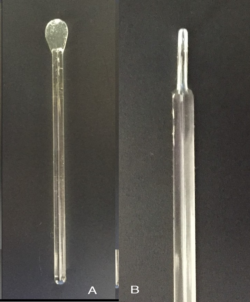
a – probe’s general view
b – side view of the flat end
- She rolls a piece of cotton on the other end of the probe.
- The end with cotton is dipped into an extract of calendula, an herb known for its antiseptic properties.
- The patient looks up, and the therapist carefully places the flat end of the stick behind the lower lid.
- The therapist applies circular and upward compression/friction strokes using her index finger and massaging the lower lid between her finger and the flat end of the glass stick. She holds the stick firmly, avoiding its contact with the eyeball.
- While she does that, discharge from the Meibomian glands appears on top of the lid, and she wipes it off with cotton dipped in calendula extract.
- In the same way, the therapist moves along the entire lower lid, and after that, she applies the same therapy to the upper lid.
- After the drainage the therapist massages both eyes while they are closed.
- At the end, the therapist places Posiformin (bibrocathol) cream on the eyelids, which has an anti-inflammatory action on mucous membranes and temporarily reduces secretion.
Video:
Eyelid massage Tarus Odessa – YouTube
I think this is a fascinating example of how a simple manual procedure can make dramatic changes in the lives of patients. This is why all of us need to work together to bring massage therapy back into traditional American medicine, where it originated and belongs.
We would like to express deep appreciation to Prof. Sergei Shchipun, MD, for his clinical expertise and willingness to share materials from his clinic with SOMI.
REFERENCES
- Linton RG, Curnow DH, Riley WJ. The meibomian glands: an investigation into the secretion and some aspects of the physiology. Br J Ophthalmol. 1961;45(11):718-723. doi:10.1136/bjo.45.11.718
- Shrestha RK, Borchman D, Foulks GN, Yappert MC, Milliner SE. Analysis of the composition of lipid in human meibum from normal infants, children, adolescents, adults, and adults with meibomian gland dysfunction using ¹H-NMR spectroscopy. Invest Ophthalmol Vis Sci. 2011;52(10):7350-7358. doi:10.1167/iovs.11-7391
Category: Medical Massage
Tags: JMS 2017 Issue #1
