
In Part I of this article, we outlined the topic of S-spine and J-spine and the degree of curvatures associated with them: PERSONAL OPINION: S-SPINE vs. J-SPINE: IS THERE ANY MERIT IN THIS DISCUSSION? PART I
Let’s now concentrate specifically on the subject of curvatures and find out if our discussion in Part I carries any support from medical and scientific sources.
As a reminder, let’s look again at two spine models: an S-spine with a ‘normal’ set of curvatures and a J-spine with flat or ‘abnormal’ curves.
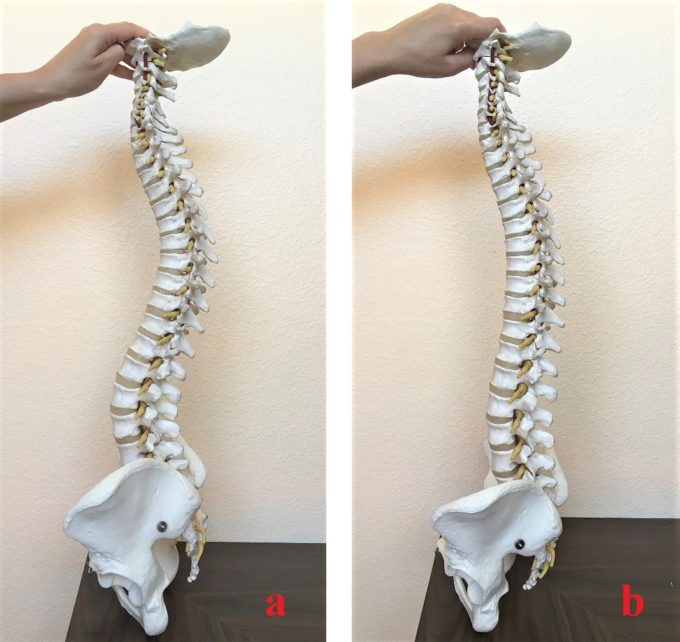
Our first video below presents the behavior of the S-spine with larger curvatures when it absorbs the impact of vertical compression load.
Our second video presents the behavior of the J-spine with smaller curvatures when the same vertical load is applied to it.
Our final third video presents the basic arrangement of the vertebral segment (two vertebrae and intervertebral disk in between) and its behavior inside of large and small spine curvatures.
SUPPORT FROM THE SCIENCE
Here are the results of several studies which support these observations. Notice that the articles are relatively recent, since this issue has just lately come onto the radar of scientists.
- Shirazi-Adl et al. (2002) clearly demonstrated that flattening of the lumbar lordosis and an increase in posterior pelvic tilt are keys to optimal posture. Both of these factors greatly diminish excessive engagement of the lumbar muscles which additionally decreases the compression load on the intervertebral disks and spreads the load more equally throughout the disks. Conclusion: With flatter curvatures, the shock-absorbing abilities of the spine itself are fully engaged with lesser help needed from the neck and back muscles to counter-resist vertical load. To the contrary, the vertebral column with larger curvatures is unable to provide full shock absorption, and the cervical and lumbar muscles become constantly engaged, especially in cases of repetitive vertical compressions (e.g., running on a treadmill). That triggers the domino principle: extra work exhausts muscles quickly – as a defense reaction, the brain increases resting muscle tone and forms protective muscle tension on top of that – increase in muscle tone diminishes action of the muscle pump – muscles experience insufficient oxygenation – lesser oxygenation diminishes ATP production which is fuel for the contraction/relaxation – less fuel is available, so more myofibrils stick together forming local muscle spasm – active trigger points become its epicenters.
- Meakin et al. (2008) used an upright positional MRI scanner to acquire lateral images of the lumbar and lower thoracic spine of 24 subjects. The subjects were imaged in standing positions while 0, 8, and 16 kg of load were applied across their shoulders using an apron. MRI showed that in those subjects who had initially smaller than average curvature, the vertical load additionally straightened their curvatures under the pressure. At the same time, those who had greater-than-average curvatures before loading showed an additional increase in curvatures under load, in other words, the entire vertebral column sank. Conclusion: The so-called ‘J-spine’ configuration gives the vertebral column a unique biomechanical ability to additionally straighten itself while the vertical load is applied. The only option the S-spine has to protect the disks and avoid their damage is to additionally increase already large curvatures. In such a case, the entire spine sinks under the pressure to absorb the impact of vertical load. Why, instead of sinking under the vertical load, does the vertebral column in people with lesser curvatures do the opposite—straighten itself? The answer is in the results of the study below.
- Pavlova et al. (2014), using modern equipment, first established the median lower back shape and determined deviations from the baseline with larger and lesser curvatures. In subjects with larger lordosis (lordotic curvature 30 degrees and above) the lower back muscles work harder trying to diminish the degree of initial lordosis. At the same time, in subjects with lesser lordosis, the lower back muscles don’t do any extra work trying to diminish large curvature and as a result the pressure is distributed more evenly within the entire vertebral column. Conclusion: Results of this study greatly support the idea that S-spine is a deviation from the original J-spine. I would like readers to pause for a second to fully acknowledge the importance of the following statement: in people with larger curvatures, or what we call normal or S-spine, their own brain, using muscle support, is constantly trying to correct and decrease these curvatures! This is why people with larger curvatures have more pain in the lower back and neck. Neck and back muscles are working a double shift trying to diminish large curvatures associated with S-spine every time we are running, walking or jumping. Chronic tension in the back and neck muscles and incorrect distribution of the vertical load through the disk are the main causes of the disk abnormalities. To the contrary, the vertebral column of people with smaller curvatures spreads the vertical load through each disk more evenly. At the same time, the neck and lower back muscles are able to support smaller curvatures by additionally straightening them while the vertical load is still applied! People with large curvatures are lacking this important mechanism of shock absorption.
IMPORTANCE OF THE SPINE ARRANGEMENT FOR THERAPISTS
It seems the topic of S-spine vs. J-spine is an abstract issue for therapists. In reality, it is very important for everyday practice from stress reduction massage sessions to clinical application of massage therapy. If smaller spine curvatures are more beneficial than what we consider the normal curvatures of the S-spine, then:
- All techniques which target ‘restoration’ of the cervical or lumbar curvatures from flatter ones, especially in younger patients, should be abandoned.
- During any treatment, the client/patient must be positioned to flatten the curvatures. In the position on the stomach, a pillow should be placed under the belly to flatten the lumbar curvature and a bolster under the feet. The cradle which supports the neck should be lowered. In the position on the back, a folded towel or small pillow (depending on the size of the cervical lordosis) should be placed under the occipital part of the head and bolsters under the knees, which are slightly spread in mild outer rotation.
- For homework to be effective the patients with any upper or lower body pain and dysfunction should at least temporarily avoid any exercise or stretching which requires neck or lower back extensions. They will increase the degree of the cervical and lumbar lordosis.
- Any exercise to strengthen posterior cervical and lower back muscles can be conducted only after pain and tension are eliminated.
DECOMPRESSION OF THE AFFECTED VERTEBRAL SEGMENT(S) WITHIN THE CURVATURES
Abnormal pressure within each vertebral segment is a result of three major forces acting on the segment: the weight of the body, the force of gravity, and the supportive pressure of the soft tissues, especially layers of powerful muscles.
There are other components which are also contributing factors, and they are equally important (e.g., protective muscle spasm developed by the brain secondarily, facet joints fixation, ATP shortage, etc.).
However, if we are talking about the initial triggers, these three factors and their imbalance are the main contributors to a gradual increase in vertical pressure which results in the disk trauma and degeneration. That brings us to a common framework of the soft tissue therapy for patients with disk bulging and herniations.
Weight
Yes, in an ideal scenario each patient with a disk abnormality should solve the extra weight issue if it is present, and indeed it can be a decisive factor to avoid further progression of disk pathology, expensive therapies and eventually spinal surgeries. We regularly observe these miracle cures of our patients who made the effort and took charge of their own health. However, it is not a quickly achievable goal and the patient in pain simply doesn’t have time to do it and can’t do any exercises because of the pain present. In such a case, weight control becomes obligatory but a future project.
Gravity
We can’t remove the force of gravity from our lives, but we can temporarily diminish its impact on the affected vertebral segment with light repetitive exercises in the swimming pool. Thus, for the treatment to be successful, and in the future as a preventive measure, all patients with disk pathologies should use light repetitive exercise in the swimming pool. In the acute stage, even floating or walking is enough.
Why is this component so important? As we know, although each vertebral segment provides separate innervation, all soft tissues, especially skeletal muscles, on the right and left sides are constantly communicating with each other via the same spinal segment. Thus, in the normal scenario, the right and left sides are working together as members of the same team. If the right-side muscles contract, the left side will relax to let movement happen.
In a patient with disk pathology the brain creates a very sophisticated system of guards and blocks to protect the spinal nerve from any additional irritation or damage. The smaller impact of gravity in the water allows the side which carries less protective tension to diminish and control the protective spasm in the muscles on the more affected side.
An additional benefit of repetitive pool exercises is restoration of ATP (muscle fuel) storage and production due to the increase of blood perfusion in the water since blood flow also is affected by the force of gravity.
Soft Tissue Decompression
The third part of the initial treatment is decompression of the soft tissues around the vertebral segment using a layer-by-layer approach to somatic rehabilitation. In the following video, let us illustrate the impact of soft tissue decompression on the intervertebral disk using the analogy of a toothpaste tube. This analogy can also be used by therapists to explain to patients what happened to them and the importance of soft tissue rehabilitation to promote recovery.
Thus, the ultimate decompression of the vertebral segment and avoidance of spinal surgery requires a special program of rehabilitation in which the abnormality is attacked from all possible directions. Yes, MM is the first step in the decompression of the soft tissue component, but other modalities (spine manipulations, acupuncture or dry needling, prolotherapy, epidural injections, etc.) must be used as well to help in obtaining stable clinical results and save the patient from an unnecessary surgical procedure.
One final piece of clinical information to consider. Disk abnormalities are the only pathological conditions in the human body which get better with age. Aging is accompanied by drying out of the gel of the nucleus pulposus, and this creates a condition called natural fusion. The outcome of it is exactly what the spinal surgeon is trying to achieve with surgery – stable fusion between the vertebrae. The only difference is that with pain-free aging, fusion between the affected vertebrae becomes a natural process and it is the therapist’s job to keep the patient out of trouble, regularly unloading the soft tissue component and eventually letting natural fusion happen.
REFERENCES
- Meakin JR, Smith FW, Gilbert FJ, Aspden RM. The effect of axial load on the sagittal plane curvature of the upright human spine in vivo. J Biomech. 2008;41(13):2850-4. doi:10.1016/j.jbiomech.2008.06.035
- Pavlova AV, Meakin JR, Cooper K, Barr RJ, Aspden RM. The lumbar spine has an intrinsic shape specific to each individual that remains a characteristic throughout flexion and extension. Eur Spine J. 2014;23 Suppl 1(Suppl 1):S26-32. doi:10.1007/s00586-013-3162-1
- Shirazi-Adl A, Sadouk S, Parnianpour M, Pop D, El-Rich M. Muscle force evaluation and the role of posture in human lumbar spine under compression. Eur Spine J. 2002;11(6):519-26. doi:10.1007/s00586-002-0397-7
Category: Medical Massage
Tags: JMS 2019 Issue #3
