
This exceptional clinical case was contributed to JMS by our student Juan Luis Ordaz Sabag, DVM, CMMP, LMT, from Mexico, who recently graduated from our Medical Massage Certification Program. Juan Luis has a long and productive relationship with SOMI and once was featured as Person of the Month in issue #3, 2015. He lives and successfully practices Medical Massage in Torreon, Mexico.
Being a Doctor of Veterinary Medicine gave Juan Luis a better and quicker understanding of the important role Medical Massage plays in patients’ treatment. He meticulously documents in pictures and notes every one of his clinical cases and the progress of their treatment. It makes his contributions to JMS priceless because readers can learn a lot from real clinical photos and the author’s notes.
While reading Juan Luis’s case, notice how creative he became with his clinical decisions. This is what we expect from our students who eventually become Massage Clinicians. It is a mistake to blindly follow the treatment protocol offered by any educational source. It puts the therapist’s mind in a box mentality, which has nothing to do with clinical reality. In medicine, including MT, nothing is written in stone! In a textbook or during class, you are presented only with average scenarios, while the clinical reality is much more complex.
The efficient therapist arranges techniques and modalities not based on recommendations from educational sources, but only on the detailed evaluation of clinical symptoms. This case is a great example of the creativity we expect from our students when we finally free their minds from the box mentality.
MEDICAL MASSAGE vs. MULTILAYERED PATHOLOGY
In May, a 36-year-old male visited our clinic with complaints about pain in the middle back and upper right shoulder, with ‘pins and needles’ sensations in his right arm and face. He also noticed that he had recently developed uncontrollable muscle jerking. He had had these sensations on and off for the previous 10 years, but in the last 12 months they had really intensified.
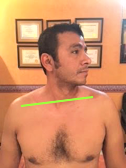
Over the past years, he had been treated by a family physician and physical therapists and had consultations with several orthopedists and neurologists. The patient was diagnosed with intervertebral disk herniations at the C3-C4 and C5-C6 levels. He also has mild lumbar scoliosis to the right. After years of different therapies, cervical surgery was recommended, which he wanted to avoid.
EVALUATION
Detailed questioning identified the following pain pattern: the patient felt acute pain in the posterior neck (especially the suboccipital area), right upper shoulder, middle back, anterior neck bilaterally, and both parasternal regions. Aching pain radiated along his entire right upper extremity. There was a burning sensation in the middle back between the scapula and vertebral column and in the hand along the ulnar nerve distribution. All of that indicated a significant sensory deficit within the distribution of many spinal nerves.
Multiple active trigger points were detected in the muscles of the right neck, shoulder and upper extremity (anterior scalene, lower and upper trapezius, rhomboids, supraspinatus, pectorals).
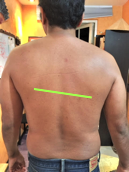
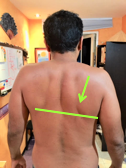
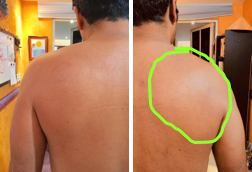
Active Connective Tissue Zones in the skin and superficial fascia were detected in the middle back and in the posterior shoulder with thickening of the skin, stretch marks and pigmentation, which suggested the presence of Cutaneous and Connective Tissue Zones in the first (skin) and second (superficial fascia) layers.
The significant restriction of the trapezius muscle’s mobility indicated the presence of Connective Tissue Zones at the third level (deep fascia) in the middle back. Periosteal trigger points were active on the spinous processes of the lower thoracic vertebrae between T9 and L1.
Wartenberg’s Test, which indicated tension in the anterior scalene muscles, was positive bilaterally, but with extreme withdrawal on the right. It pointed to the irritation of both brachial plexuses, with compression on the right.
The Motor Test on the right showed hand weakness in the Ulnar and Radial Nerve Distributions. The X-ray indicated the presence of mild right-sided scoliosis.
Here are visual observations of my patient before treatment:
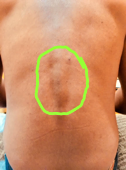
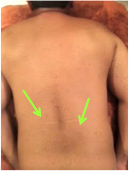
TREATMENT
It was obvious that over the years, the patient had developed a chronic, multilayered pathology, and it had to be approached as a mix of reflex and local abnormalities. To address all issues and leave no stone unturned, I decided to combine treatment protocols suggested by the Science of Massage Institute and base their mix on the data I obtained during the patient’s evaluation.
I started with the application of the Anterior Scalene Muscle Protocol to free the brachial plexus from irritation and after that added the Trapezius Muscle Syndrome Protocol. Thus, first of all, I targeted the reflex component of my patient’s clinical picture. Following two treatments, the patient reported less tension in the neck, upper and middle back. The uncomfortable sensations in the upper extremity were still present.
The patient also exhibited great sensitivity along the 5th-10th intercostal spaces on the right side, and to address that, I decided to add elements of the Rhomboideus Muscle Syndrome protocol. As a result of the application of the combined treatment, I noticed a significant decrease in the fascial tension and restoration of skin elasticity in the middle back, and the patient reported that he no longer felt tingling and numbness in the right side of the face.
After two more sessions, Wartenberg’s Test became negative, which meant that the ASM had freed the brachial plexus from direct irritation. The patient had mild to moderate sensory abnormalities only on the forearm and hand, with full restoration of sensations on the back, shoulder and arm.
Considering the weakness of the posterior shoulder muscles, I added elements of MEDICAL MASSAGE PROTOCOL for Rotator Cuff Syndrome. After the adjusted treatment, I noticed improvements in the skin’s elasticity and complete disappearance of fascial tension in the right posterior shoulder, which was a very prominent symptom from the very beginning. Also, the function of his posterior shoulder muscles started to slowly improve.
At this point, the patient added active exercises and yoga to energize and revitalize the soft tissues and restore balance between both divisions of the autonomic nervous system. As a result of the combined treatment and rehabilitation strategy, the only symptom the patient exhibits at this point is an occasional tingling sensation at a level of 1-2 on his right hand. I expect this symptom to fade away slowly while the ulnar and radial nerves continue to recover from chronic irritation.
Here are the visible changes in my patient that I recorded after the therapy:
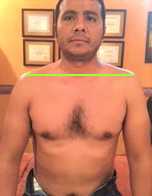
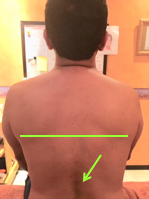
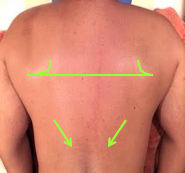
What was interesting and unexpected was that the patient’s skin showed a significant decrease in the intensity of the dark pigmentation over the spinous processes of the lower thoracic vertebrae. That meant that the initial pigmentation was indeed a consequence of cutaneous reflex zone formation. I freed the cutaneous branches of the T9-L1 spinal nerves from irritation by tight fascia and restored normal innervation of the matching dermatomes, and the skin regained its elasticity and even color.
Category: Case Studies
Tags: JMS 2018 Issue #3
