
The purpose of this section of the Journal of Massage Science is to inform the practitioners about valuable articles that frequently go unnoticed, as well as to point to those authors and publications who exhibit low educational standards. We do not play politics, and we are not associated with any publishing company or professional association. We are a completely independent voice and we promise you direct, unbiased reviews based strictly on the science.
If the author of the reviewed article does not agree with our opinion, we will be more than happy to publish his or her response and have a productive discussion over the article’s subject.
At the end of the year, we will recognize and reward the author of the most important publication(s) and point to the authors of the most unscientific publication(s). We hope this will help to raise the bar of published materials in massage journals for the benefit of the entire profession.
MASSAGE & BODYWORK MAGAZINE

The Loudest Voice Wins. Massage & Bodywork Magazine, Jan/Feb: 30-31, 2018
While this looks like a very simple and unimportant article, clinically speaking, the author illustrates a very important issue. Very frequently, successful treatment of the original symptoms the patient came in with coincides with the appearance of new symptoms in parts of the body that look completely unrelated.
The author is completely correct when he explains in this piece an important clinical observation: the decrease in intensity of the original symptoms will make the symptoms that were hiding behind the original ones clinically prominent. This scenario confuses patients since they may think that, despite improvements, the treatment triggered new symptoms. In reality, the author has correctly labeled it: The Loudest Voice Wins.
Common Side Effects of a Common Drug. Massage & Bodywork Magazine, Jan/Feb: 40-43, 2018
This article raises a very important topic for therapists, and we observe it daily in our clinic and clinics associated with SOMI. Patients who take statins regularly complain about various musculoskeletal syndromes. Therapists should be aware of it since their therapy may fail because the initial trigger, statins, is still in the body.
Force Distribution in the Foot. Massage & Bodywork Magazine, Jan/Feb: 44-45, 2018
A small but very good article which covers the biomechanics of the foot.
The Posture Window. Using Posture to Guide Assessment and Treatment. Massage & Bodywork Magazine, Jan/Feb: 68-75, 2018
The article raises a lot of important points which can be summarized as follows: Postural Changes are responsible for patients’ pain and discomfort, and working on the soft tissues while postural changes are not addressed greatly diminishes the clinical effectiveness of MT.
Yes, the author is correct here, but only in a minority of clinical cases. Based on our clinics’ combined experience, it is approximately 20%. Thus, postural changes may trigger symptoms the author mentioned. However, in the majority of cases, the postural changes are developed by the brain as a secondary reaction to the chronic pain. In such cases, addressing the postural changes themselves also becomes a waste of time and effort since the initial trigger must be identified and eliminated first before postural changes should even be considered.
Exploring the Dorsal Scapular Nerve. Massage & Bodywork Magazine, Jan/Feb: 88-91, 2018
Great article!
Release the Parking Brake and See What’s Driving the Muscle Spasm. Massage & Bodywork Magazine, Jan/Feb: 92-93, 2018
Good article.
Squamous Cell Carcinoma. More Than Meets the Eye. Massage & Bodywork Magazine, Mar/Apr: 42-45, 2018
The topic of this article is very important, but the article itself misses vital information. Squamous Cell Carcinoma (SCC) is a relatively aggressive skin cancer which must be diagnosed asap. It allows the dermatologist to achieve quick and stable clinical results. The article is dedicated to this topic, and the author is correct when she states that:
“Massage therapists have a unique privilege: we see more of our clients’ skin (especially on the posterior surface of the body) than they do themselves, and with regular clients, we see that skin over the course of time.”
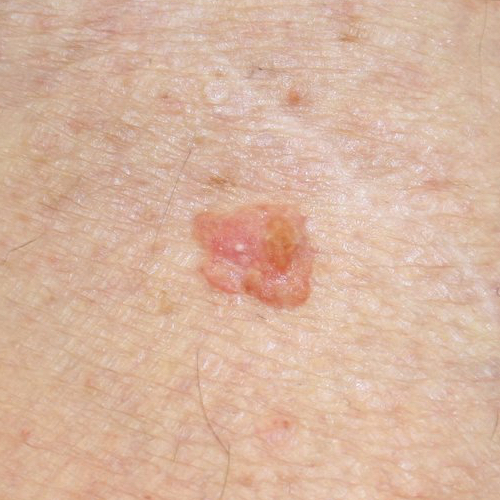
However, nowhere in the article does the author actually show therapists a picture of what the early stages of SCC look like. If the article doesn’t provide a correct image of SCC, the entire goal is diminished to the level of basic info without ANY clinical significance. This is the weakest part of the article. Considering the importance of the subject the author raised, but didn’t follow through with, we decided to fill the informational gap in the article and show a picture of the early stages of SCC.
Intervertebral Disks. Massage & Bodywork Magazine, Mar/Apr: 47-48, 2018
A very good introductory article on intervertebral disks.
De-Rotators and Other Muscles That Change Their Joint Actions. Massage & Bodywork Magazine, Mar/Apr: 82-89, 2018
Simply EXCELLENT article!
Guyon’s Canal Syndrome. Massage & Bodywork Magazine, Mar/Apr: 94-97, 2018
A very good article on a rarely mentioned subject.
MASSAGE TODAY
Understanding the Gamma Efferent System. Massage Today. 18(1), 2018
A very good article!
Restoring Vagal Tone: Improving Your Clients’ Quality of Life. Massage Today. 18(1), 2018
This article covers the important subject of balance in the activity of the autonomic nervous system, specifically the increase in the parasympathetic or vagal tone. This subject is especially important in light of new convincing evidence that the body doesn’t have a sacral parasympathetic division as we all previously thought.
We have only one concern – that the article heavily relies on the Polyvagal Theory proposed by S.W. Porges, PhD. This theory is definitely ‘food for thought’ and a great point to start discussion, but at the same time it is just a theory based mostly on circumstantial evidence. However, we agree with the authors that extending learning, including Polyvagal Theory, will widen therapists’ intellectual horizons.

Could Massage Spread Cancer in the Newly Diagnosed? Massage Today. 18(1), 2018
To read the review, see RESPONSE TO NEW CRITIQUE BY T. WALTON PUBLISHED IN MASSAGE TODAY.
TMJ: A Case Study, Treating Beyond the “Dental Approach.” Massage Today. 18(2), 2018
The author is completely correct when he states that the dental-only approach won’t be able to deliver stable clinical results for patients with TMJ Dysfunction. However, he is mistaken again when he discusses the treatment options.
Mr. McCann considered various biomechanical changes in his patient with TMJ dysfunction as indicators of the tension inside the TMJ built up as a result of pelvis rotation, chest twist, shoulder elevation, etc. Clinically speaking, the author puts the chicken before the egg, since all these biomechanical abnormalities in the majority of cases are secondary developments triggered by the brain as a reaction to chronic nociceptive stimuli that bombarded his patient’s brain for some time.
Why, in such a case, did Mr. McCann’s treatment work, and why was he able to help his patient with TMJ Dysfunction? As the author reported in this case study, his patient also suffered from chronic headaches. In such a case, the trigger for the headaches and TMJ dysfunction was more likely mild irritation of the minor occipital nerve by the posterior cervical, scalene and sternocleidomastoid muscles. Here is a quote from the article where the author describes his treatment routine during the first session:
“The first myofascial soft tissue protocol was applied to bring the shoulders and neck back, release the scalenes and sternocleidomastoid so the neck could straighten, and release the back of the neck down to the shoulders so they could drop and balance.”
We bet that this treatment was a key to the author’s success since we observed an almost identical response from our patients to similar therapy for patients with TMJ dysfunction triggered by Minor Occipital Nerve Neuralgia. Freeing the minor occipital nerve will deliver quick results, and addressing the pelvis and chest (as the author did during the following sessions) targeted secondary biomechanical and postural syndromes, which in many cases will fade away by themselves if headache and TMJ pain are not factors anymore.
So, without fully understanding what actually happened to the patient, the author used an initially correct treatment strategy, which had nothing to do with his views of the necessity of addressing secondary symptoms as the main treatment option.
Readers may have a reasonable question: What is the difference? The author helped the patient, and this is what counts.
Working with TMJ patients on a daily basis, we are sure that correct evaluation is the key to the correct treatment option. The author made a mistake in evaluation, but ironically used the correct treatment option. However, it can’t always be the case since identifying the initial trigger of the somatic abnormality is the foundation of 100% effective somatic rehabilitation.
Meet the Popliteus: A Cause for Knee Pain. Massage Today. 18(2), 2018
We think that for the MT to be fully accepted as a legitimate part of somatic rehabilitation and become part of medicine we all should agree on at least some basics. If there is no unified vision on simple things, how can therapists present their case to other health practitioners? There is no way in any other part of medicine one can find completely different pieces of information regarding the same topic. We regularly observe this phenomenon among authors and educators who are addressing the clinical aspects of MT. This article is a great example of such an unfortunate trend.
The article is dedicated to the role of the popliteal muscle in the generation of knee pain. Here are three aspects which are erroneously presented in the article:
- Let’s start with the action mentioned in the article for the popliteus muscle:
- Knee flexion
- Lateral rotation of the femur
- Medial rotation of the tibia/fibia
We can produce other sources which will show that the author is incorrect, but let’s use Dr. Travell and Dr. Simons’ Trigger Point Manual (1983), as it is widely used and respected by therapists and other health practitioners. Here is a quote from the book from pages 342-343:
“The popliteus muscle is at mechanical disadvantage for producing knee flexion by virtue of the angulation of its fibers and their proximity to the axis of rotation of the knee.”
Both authors also cited several studies which examined the popliteus muscle using electromyography, and all authors found that the muscle first of all produces medial rotation of the leg. Its participation in knee flexion is minimal. Unlocking the knee joint from extension, which the author mentioned in the article, happens first of all because of the lateral rotation of the femur during weight bearing (Travell and Simons, 1983). Thus, the popliteus muscle very weakly supports knee flexion mentioned in the article in the first position, while its main action is medial rotation of the leg.
- The article mentioned tension in the popliteus muscle as an independent pain syndrome. In reality, this is not the case. Isolated tension in the popliteus muscle is a very rare event, and in the majority of clinical cases, pain in the popliteus muscle is due to the mild irritation of the tibial nerve, which supplies the popliteus muscle as well as other leg muscles. Here are Travell and Simons again:
“…popliteus rotates distal part of the limb and seldom presents as a single-muscle myofascial syndrome.”
- The pain location mentioned in the article is completely wrong. Here is a quote from the article:
“If they’re complaining of pain on the medial and/or front of the knee, especially when they run, walk up stairs, or downhill, those are also signs that palpating the popliteal fossa is a good idea.”
Let’s look at Fig. 2 (Fig. 17-1 from Travell and Simons, 1983), which indicates a pain pattern generated by the tension in the popliteus muscle.

Fig. 2. Referred pain pattern of a trigger point (X mark) in the right popliteus muscle We ask readers to match the information in the picture with the quote from the article which indicates that the patient with tension in the popliteus muscle will exhibit pain on the “medial and/or front of the knee” as the author suggests.
Let’s, for the sake of discussion, consider that the author will make the point that Travell and Simons’ textbook is an old publication. Let’s look at the same topic in recent medical literature.
Chang et al., (2016) used Ultrasonography to examine, as they put it, “Uncommon cause of posterior knee pain [bold by JMS]” generated by a tense popliteus muscle.
Cho et al., (2016) reported a very rare case of the tibial nerve compression by an enlarged popliteus muscle with all symptoms located on the posterior [bold by JMS] knee and leg.
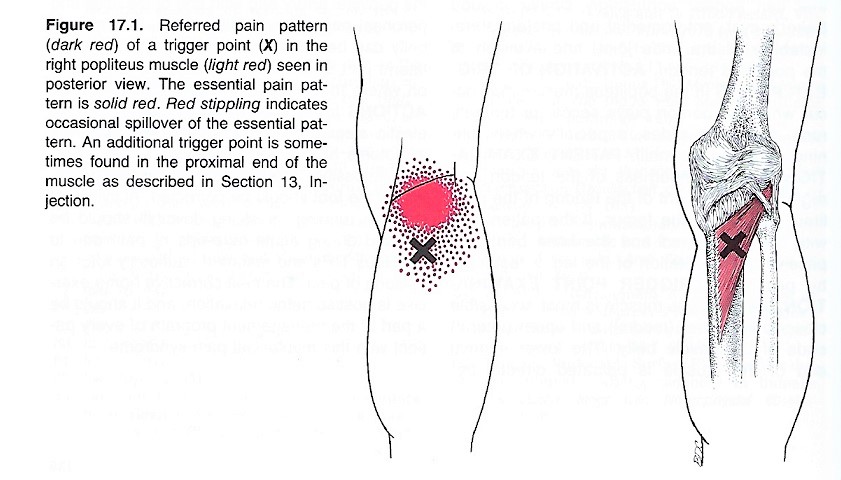
As readers may see, the article provides completely misleading information about the nature of tension in the popliteus muscle, but, what is more important, it misleads therapists in evaluation and eventually treatment options, since if the evaluation is done incorrectly, the therapist will make treatment mistakes.
What is really upsetting is such low writing standards exhibited by the author who addressed the clinical issue with erroneous assumptions and didn’t even bother to do a basic Google search before writing a piece for a national publication on a clinical subject.
If we can’t agree on such basics as where pain in case of tension in the popliteus muscle is located, who in the medical profession will listen to our pleas about the clinical effectiveness of MT?
REFERENCES
- Chang KV, Hsiao MY, Hung CY, Özçakar L. An uncommon cause of posterior knee pain: diagnosis and injection for popliteus strain using ultrasonography. Pain Med. 2016;17(4):795-796. doi:10.1093/pm/pnv037
- Cho KJ, Kang S, Ko S, Baek J, Kim Y, Park NK. Neurovascular compression caused by popliteus muscle enlargement without discrete trauma. Ann Rehabil Med. 2016;40(3):545-550. doi:10.5535/arm.2016.40.3.545
- Travell JG, Simons DG. Myofascial Pain and Dysfunction: The Trigger Point Manual. Williams & Wilkins; 1983.
Muscles & Tendons of the Thumb. Massage Today. 18(2), 2018
A good article on the anatomy of thumb muscles.
Scapulohumeral Rhythm: Looking Beyond the Glenohumeral Joint. Massage Today. 18(3), 2018
A very informative article on coordinated movements between the scapula and shoulder joint.
Lymphatic Balancing: The Six-Step Treatment Approach. Massage Today. 18(3), 2018
The author is completely correct when he emphasizes the frequently overlooked point that Lymph Drainage Massage is not only helpful in cases of edema, but it must be a component of every clinical application of MT. LDM is indeed the structural component of each Medical Massage Session.
MASSAGE MAGAZINE
Massage Treatment Planning for the Diabetic Client. Massage Magazine, issue 261: 36-42, Feb, 2018
This is a very introductory article on Diabetes and the indications and contraindications for MT applied to the diabetic patient.
Neural Manipulations. Massage Magazine, issue 261: 48-50, Feb, 2018
This article is on an important clinical subject, but the piece itself gives extremely limited information for readers. At least some general outlines or examples would be excellent additions. Without them, the article has very limited practical value.
Lymphatic Liquefaction Using Vacuum Cups. Massage Magazine, issue 262: 50-53, Feb, 2018
This article is a rare piece on the correct application of vacuum as part of rehabilitation.
Category: Good Apples, Bad Apples
Tags: JMS 2018 Issue #1
