
The high clinical effectiveness of Medical Massage, when it is correctly practiced, brings a large number of very complex cases to the clinic, since many desperate patients try to find solutions to their pain and suffering after everything else they tried has failed. We observe that in our practice as well as in the clinics of our former students who successfully practice Medical Massage around the country. This case is a perfect illustration of that.
MEDICAL MASSAGE vs. YEARS OF SUFFERING AFTER THYROID CANCER SURGERY
Approximately two months ago, we had a new patient in our clinic. She was a 52-year-old, physically fit female who complained of acute pain in the left neck and upper shoulder, severe restriction of cervical rotation to the left, pain in the left shoulder joint, a left-sided headache and weakness of the left arm. She had had these symptoms on and off for approximately the last 5 years and had gone through all available therapies without stable results. Her PCP suggested that she see a pain specialist, and the only solution offered to her was an opioid prescription. She completely rejected this proposal.
Her friend, our former patient, tried for a long time to convince her to visit our clinic, but she always declined, saying that she had already wasted a lot of money on massage therapists, chiropractors and physical therapists without any success. Finally, our former patient succeeded, and that is how she got to our clinic. During the clinical interview, we learned that she owned a small company that installs irrigation systems in backyards, and she thought that the recent flare-up was a result of her digging trenches due to an employee shortage.
EVALUATION
The large scar on her neck indicated extensive thyroid gland surgery. Indeed, according to the patient, 5 years ago she had thyroid cancer, and the left half of her thyroid gland was removed. However, two days later the surgery was repeated, since the pathology report indicated that the surgeon didn’t get a clear margin the first time. During the second surgery, her entire thyroid gland was removed. Following the second surgery, she developed an extensive keloid scar, and in an attempt to soften it, the scar was injected with steroids, but it didn’t work, and she had two plastic surgeries to make the scar cosmetically acceptable. Fig. 1 shows a picture of our patient’s anterior neck. The large horizontal scar runs through her entire neck.
During the visual observation of the anterior neck and shoulders, it was obvious that her left upper shoulder was elevated and there was up to a 30% increase in the thickness of the muscle mass on the left anterior neck (see Fig. 1). Since the patient is right-handed, her right anterior neck should be 15–20% larger than the left, while it is obvious from the picture above that her left anterior neck is at least 15% more prominent.
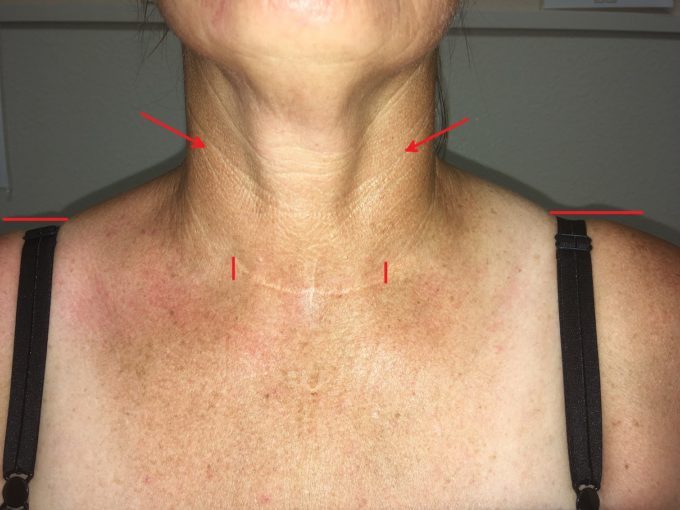
Horizontal lines – indicate shoulder levels
Arrows – point to the visible difference in the muscle mass on the left and right sides of the patient’s neck
Vertical lines – indicate the size of the scar
Palpatory Evaluation Indicated:
Wartenberg’s Test – extremely positive, with pain and numbness shooting down the patient’s left arm, forearm and thumb.
Sensory Test indicated a sensory deficit within the radial and axillary nerve distributions.
Movement Test showed a weak hand grasp, especially with her thumb.
All of these indicated the significant compression of the upper part of the brachial plexus by the Anterior Scalene Muscle, with secondary symptoms of Axillary (pain in the left shoulder joint) and Radial (pain in the neck, upper shoulder and down to her thumb) Nerve Neuralgias.
Considering the size of the scar, the repeated surgeries and the start of her symptoms after the neck operation, it was more likely that scar tissue in the area of the thyroid surgery was the reason for the tension that developed in the left ASM, and that this was the initial trigger of her symptoms.
TREATMENT
Based on the results of the evaluation, we started with the application of the MEDICAL MASSAGE PROTOCOL for Anterior Scalene Muscle Syndrome. The treatment targets the posterior neck first, since this addresses the origin of the ASM’s innervation, before moving to the anterior neck and working on the ASM directly. To decrease protective muscle tension in the posterior cervical muscles and inhibit the pain-analyzing system, as a part of the treatment we used electric vibration. As soon as the massager was placed on the left posterior shoulder, the patient almost immediately started to cough spasmodically. Interestingly enough, she started coughing (less intensely) even when electric vibration was applied to her right upper shoulder (see video below).
Such a reaction was a clear indication that scar tissue and/or tension in the ASM irritated the patient’s superior laryngeal nerve, which is a sensory branch of the vagus nerve. Normally, this nerve is located on the thyroid gland, and it triggers the cough reflex when it is irritated by direct pressure (in our patient’s case, by vibration) or when sensory receptors in the larynx, trachea and bronchi are activated by various irritants (dust, fumes, smoke, etc.). Fig. 2 illustrates the anatomy of the superior laryngeal nerve.
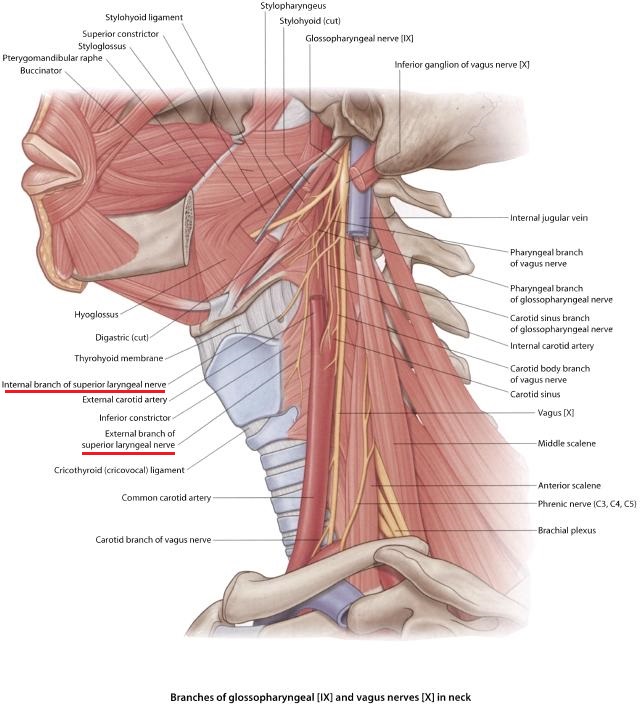
Considering the cough reaction to even distant application of vibration, we added work in the area of the scar to the ASM protocol. Immediately after the treatment, the patient felt a significant decrease in pain intensity in the left neck and upper shoulder and an increase in cervical rotation to the left.
After finishing the session, the patient was given homework, and she was informed that since she had significant tension in the anterior neck, there was a very big chance that she would have extra uncomfortable sensations the next morning. The patient was scheduled for the second session in a day.
When she came to the clinic for the second session, it was obvious that she was not at ease. Her answer to the question “How are you doing?’” triggered very unusual response. She said that she was very afraid of the treatment and that initially she hadn’t even wanted to come because of what had happened to her the morning after the first session. We expected that she would complain about extra pain and discomfort, but instead she said that after she woke up the next morning, she had completely lost the ability to swallow any food. The only things she was able to swallow were her own saliva and a small amount of water. After two hours of repeated attempts, she really panicked and decided to go to the emergency room. Just before she and her husband were ready to leave, she noticed that her swallowing had slightly improved, and eventually it was restored. She decided to come back to the clinic only because she felt significant relief of the neck and shoulder pain, relief she hadn’t felt for the last couple of years.
The patient’s next-day reaction to the first session completely changed the priorities of the therapy. It was obvious that the scar itself, her hyoid bone and her larynx had to be addressed first, but it was a tough sell to the patient, because she panicked even at the thought that what she had experienced might occur again.
We asked her if she or members of her family had noticed that her voice had changed after the surgery. This simple question took her by complete surprise. She answered “Yes! It became much lower… How do you know?”
She was really taken by surprise that we asked about her voice. She said that initially friends who hadn’t seen her for a while after the surgery mentioned that she now spoke in a lower voice. Using this piece of information, we explained to the patient what had happened and how we could help her. She reluctantly agreed. Evaluation of the hyoid bone showed that the soft tissues around it were so tight that the bone had almost lost its ability to be shifted laterally.
We now concentrated on the anterior neck only. We started working on the scar, applying skin kneading, stretching and skin rolling in different directions. To reduce tension in the soft tissues around the hyoid bone, we worked on the small muscles that form the floor of the mouth and on their insertion into the upper edge of the hyoid bone (see Fig. 3). We used draining effleurage, gentle circular friction, pinching kneading. To reduce tension in the thyrohyoid membrane, we applied gentle repetitive compression below the hyoid bone in the narrow space between the bone and the thyroid cartilage.
Next, we stretched the soft tissues inserted into the hyoid bone by moving it laterally in both directions during the patient’s exhalations. At the end, using the thumb and index finger placed on the sides of the hyoid bone, we stabilized it and asked the patient to swallow repeatedly while we tried to resist bone elevation during each swallow. At the end of this modified session, the patient was in tears over how light her entire neck felt. We informed her that there was a strong possibility that she might experience difficulties with swallowing the next morning.
At the beginning of the third session, she was very happy because she felt only residual pain in the left arm and shoulder, and while difficulties with swallowing had indeed appeared in the morning, they were gone half an hour after she took a hot shower and stretched.
After the 4th session, the patient reported that her swallowing hadn’t changed the next morning and that she no longer felt any pain or discomfort in the left neck and upper shoulder. Also, she had no headache. One more session was performed to give better stability of the clinical results, and the patient was scheduled for an appointment in two weeks.
We saw the patient two weeks later for a follow-up. She had done her homework regularly, and she didn’t have any pain or discomfort in the neck, upper shoulder and arm. However, the really interesting change was that she had started to get her normal voice back. Even her husband noticed that she now spoke in a higher voice, and she was very excited by this new and, for her, unexpected development.
LESSONS
- In every case of chronic pain, the therapist faces a chain of pathological events that needs to be understood. Only then is he or she able to choose the correct treatment to help the patient. Let’s place all the events of this clinical case in sequence.
Repetitive surgeries and steroid injections —-> formation of extra scar tissue on the anterior neck and its hardening —-> mild irritation of superior laryngeal nerve —-> increased tension of the mouth floor muscles above hyoid bone —-> restriction of hyoid bone mobility during the swallowing —-> changes in the tone of voice due to the pressure on the voice box —-> increased tension in the left ASM —-> irritation of the upper part of brachial plexus —-> tension in the muscles innervated by the affected part of the brachial plexus —-> acute pain in the left neck and upper shoulder and cervical ROM restriction.
With this complex chain of events, the actual symptoms that brought the patient to our clinic were pain and discomfort in the left neck, shoulder and arm. In the majority of cases of chronic somatic abnormalities, therapists face multi-layered pathology, and only its elimination layer by layer gives stable clinical results.
- If the therapist blindly follows the patient’s complaints without evaluating the soft tissues on a layer-by-layer basis, he or she will frequently address the secondary syndromes instead of identifying the initial trigger. In the majority of chronic pain syndromes, what is on the surface is not what needs to be treated first, since the real trigger is frequently hidden in a completely different part of the body. Our patient didn’t complain about any discomfort in the anterior neck. Instead, all her symptoms were in the upper shoulder and neck. It seems that everyone who treated her before followed her complaints, and that only patched her problems.
- If new and sometimes unexpected symptoms (disruption of swallowing in our patient’s case) appear during the treatment, they need to be addressed immediately and the treatment strategy adjusted. Such new developments pop up because the compensatory reactions developed by the brain to cope with somatic abnormalities were removed during the therapy, and a hidden, sometimes even more complex problem has now fully surfaced.
- Why did our patient have swallowing problems of such intensity? Such a seemingly simple act as swallowing is the result of complex coordination between many structures, and it clearly splits into three phases: oral, pharyngeal and esophageal. In our patient, the pharyngeal phase was greatly affected. First, let’s examine the anatomy of the suprahyoid muscles presented in Fig. 3.
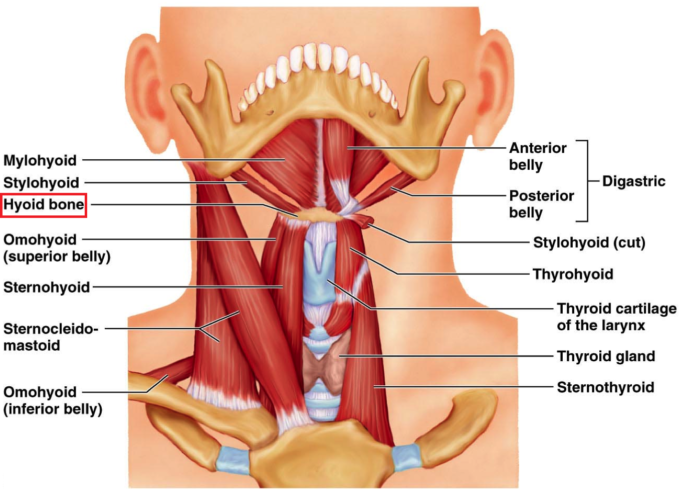
The hyoid bone (emphasized by a red square in Fig. 3) is the only bone in our body that is not attached to any neighboring bone. It is suspended in the anterior neck, and its position is controlled by the tension and sophisticated coordination of the suprahyoid muscles.
Just before a bolus of food enters the pharynx, the epiglottis must close the larynx to prevent food or liquid from entering the voice box and later the trachea. In such cases, we experience so-called physiological apnea, a stop of breathing, every time we swallow food. For the bolus of food to proceed further down, the pharynx needs to be widened and elevated. This is done by the muscles that form the floor of the mouth: suprahyoid, digastric, stylohyoid, etc. A critical element of this process is the elevation of the hyoid bone.
In our patient, as a result of the repeated surgeries and scar tissue development, the intimate coordination between the anterior neck muscles, including the suprahyoid muscles, was affected, and to deal with it, the brain adjusted their actions, while their normal elasticity was sacrificed and changed as a result of protective muscle tension that formed secondarily.
The first treatment session decreased protective muscle tension in the anterior neck, and it left the motor cortex confused for some time before it was able to regain full control over the action of the suprahyoid muscles. The patient felt it as a problem with swallowing that she hadn’t had before the first session. Her repeated swallowing attempts the next morning gave the motor cortex time to restore full coordination between the suprahyoid muscles, and they reestablished normal elevation of the hyoid bone during each swallow.
When the suprahyoid muscles exhibit tension, they may also exert pressure on the voice box, and this can contribute to a change in its normal tone. As was shown by Sullivan et al. (1997), massage therapy reduces tension in the laryngeal muscles, restores their coordination and brings back the patient’s normal voice. This is exactly what happened to our patient as well.
REFERENCES
- Sullivan SJ, Blumberg J, Lachowicz C, Raymond D. Does massage decrease laryngeal tension in a subject with complete tetraplegia? Percept Mot Skills. 1997;84(1):169-170. doi:10.2466/pms.84.1.169-170
Category: Blog
Tags: JMS 2018 Issue #3
